Breaking

Category: Health

  • Best Over-the-Counter Remedies for Texas Seasonal Allergies

    Best Over-the-Counter Remedies for Texas Seasonal Allergies

    If you live in Texas, “seasonal” allergies is a cruel joke — there is practically no season without pollen. Mountain cedar blankets Central Texas in winter, oak explodes across the state in spring, grasses take over summer, and ragweed closes out the fall. Texans deal with one of the longest and most intense allergy calendars in the country, which means the question is not just which over-the-counter remedy works, but which one works for Texas’s specific, relentless pollen assault. The good news: the best OTC options are well-studied, inexpensive, and available at any Texas pharmacy — you just need to match the right remedy to your symptoms.

    Why Texas Allergies Are a Special Case

    Texas combines several allergy aggravators: a huge landmass with diverse pollen sources, warm temperatures that stretch pollen seasons for months, and notorious super-pollens like mountain cedar (actually a juniper, Juniperus ashei) that can produce visible clouds of pollen in December and January. Cedar fever — the local name for mountain cedar allergy — hits with fatigue and body aches so flu-like that people regularly mistake it for illness. Add oak pollen so thick it coats cars yellow in March and April, plus year-round mold in humid East Texas and the Gulf Coast, and you get a state where allergy sufferers often need daily management for most of the year.

    This matters for choosing remedies because short-course thinking fails in Texas. A medication you tolerate well enough for two weeks in April might be miserable by August if it causes drowsiness or dryness with daily use. The strategy that works here is a sustainable daily regimen during your personal worst months, not sporadic pill-popping. The American Academy of Allergy, Asthma and Immunology provides pollen-type guidance that helps Texans identify which seasons hit them hardest.

    The First-Line Winners: Daily Non-Drowsy Antihistamines

    For most Texas allergy sufferers, the foundation is a second-generation oral antihistamine taken daily: cetirizine (Zyrtec), loratadine (Claritin), or fexofenadine (Allegra). All three block histamine without the heavy sedation of older drugs like Benadryl (diphenhydramine), which should be reserved for occasional nighttime use, not daily management — it impairs driving and cognition more than most people realize, and its effect wears off in hours.

    Among the three, differences are modest but real. Cetirizine tends to work fastest and strongest for many people but causes mild drowsiness in a minority. Fexofenadine is the least sedating of all and a favorite for people who need to stay sharp, though it must be taken on an empty stomach (fruit juice notably reduces its absorption). Loratadine sits in the middle — gentle, well-tolerated, slightly less potent for some. In Texas’s heavy pollen, many allergists suggest starting with cetirizine or fexofenadine. Buy the store brand; the generics are chemically identical and cost a fraction of the name brands. Take it daily and consistently — antihistamines work best as prevention, not rescue.

    Nasal Sprays: The Most Underused OTC Powerhouse

    Here is what many Texans miss: for nasal congestion, sneezing, and runny nose, steroid nasal sprays outperform oral antihistamines. Fluticasone (Flonase), triamcinolone (Nasacort), and budesonide (Rhinocort) are all available OTC, and they reduce nasal inflammation directly at the source. They take a few days of consistent use to reach full effect — this is the number one reason people declare they “don’t work” — so start them before your bad season peaks and use them daily.

    Technique matters enormously: aim the spray outward, toward your ear on each side, not straight up the middle (which irritates the septum and causes nosebleeds). A gentle sniff, not a hard snort. For fast relief while the steroid builds up, pair it with a saline rinse — a neti pot or squeeze bottle with distilled water flushes pollen physically out of the nasal passages and is one of the highest-value, lowest-cost allergy interventions available. Antihistamine nasal sprays like azelastine (Astepro, now OTC) work faster than steroids for some people and can be combined with them during brutal weeks.

    Eye Symptoms, Congestion, and the Supporting Cast

    Itchy, watery eyes respond best to antihistamine eye drops — ketotifen (Zaditor, Alaway) is available OTC, works within minutes, and lasts up to 12 hours. Oral antihistamines help eyes somewhat, but the drops target the symptom directly. For severe congestion, pseudoephedrine (Sudafed, behind the pharmacy counter — you will need ID) is the most effective oral decongestant, but it can raise blood pressure and disrupt sleep, so it is a short-term tool, not a daily solution. Avoid oxymetazoline nasal sprays (Afrin) for more than three days; rebound congestion from overuse is worse than the original problem.

    A few Texas-specific tactics round out the regimen: shower and change clothes after spending time outdoors during peak pollen, keep windows closed and run air conditioning with clean filters during your worst months, and check daily pollen counts — many Texas cities publish them, and planning outdoor exercise for low-count times (often after rain) genuinely helps. An indoor HEPA air purifier in the bedroom reduces overnight exposure, which matters because nighttime congestion ruins sleep quality. The Asthma and Allergy Foundation of America offers practical pollen-avoidance strategies tailored to high-pollen regions.

    When OTC Is Not Enough

    See an allergist if your symptoms persist despite a proper daily regimen (antihistamine plus nasal steroid used correctly for two to three weeks), if you need decongestants regularly, if allergies trigger asthma symptoms or sinus infections, or if poor sleep from congestion is affecting your life. Texas allergists can do testing to identify your specific triggers and may recommend immunotherapy — allergy shots or sublingual tablets — which actually retrain your immune system over three to five years and are the only treatment that modifies the disease rather than masking symptoms. For lifelong Texas residents with severe cedar or grass allergies, immunotherapy is often life-changing and worth discussing early rather than after years of suffering.

    For Texas’s year-round pollen assault, the best OTC strategy is a daily non-drowsy antihistamine (cetirizine or fexofenadine) plus a steroid nasal spray (fluticasone) used consistently — not just on bad days. Add ketotifen eye drops for itchy eyes and saline rinses for congestion. Start nasal steroids before your worst season peaks, and see an allergist if a proper regimen still leaves you miserable.

    Conclusion

    Texas allergies demand a Texas-sized strategy: daily, consistent, and matched to the state’s brutal pollen calendar. Build your foundation with a generic non-drowsy antihistamine and a steroid nasal spray used correctly, add targeted help for eyes and congestion, and support it all with pollen-avoidance habits like showering after outdoor time and running filtered AC. Buy generics, use nasal sprays daily rather than as rescue, and do not settle for months of misery — if the OTC regimen is not cutting it, an allergist and immunotherapy can change the equation entirely. For more health coverage tuned to real life, browse our health section, learn about our editorial standards, or tell us your cedar fever survival tips.

    Frequently Asked Questions

    What is the best OTC allergy medicine for Texas pollen?

    A daily second-generation antihistamine — cetirizine (Zyrtec) or fexofenadine (Allegra) — combined with a steroid nasal spray like fluticasone (Flonase). The antihistamine handles sneezing and itching; the nasal spray is superior for congestion. Use both daily during your worst months, not just on bad days.

    Why do steroid nasal sprays seem not to work for me?

    They take several days of consistent daily use to reach full effect, and most people quit too early or use poor technique. Aim the spray outward toward your ear, not straight up, use a gentle sniff, and give it a full week before judging. Starting before your peak season helps enormously.

    What is cedar fever and how is it different from a cold?

    Cedar fever is the local name for mountain cedar pollen allergy, peaking December through February in Central Texas. It causes sneezing, itchy eyes, congestion, plus fatigue and body aches that mimic the flu. Unlike a cold, there is no fever, symptoms persist for weeks, and they track with high cedar pollen counts.

    Is it safe to take allergy medicine every day for months?

    Second-generation antihistamines and steroid nasal sprays are designed for long-term daily use and have strong safety records. Avoid daily Benadryl (impairs cognition) and limit decongestants like pseudoephedrine or Afrin to short courses. If you need daily medication most of the year, discuss it with your doctor or an allergist.

    Should I buy name-brand or generic allergy medicine?

    Generic. Store-brand cetirizine, loratadine, fexofenadine, and fluticasone are chemically identical to the name brands and regulated to the same standards, at a fraction of the price. The active ingredient is what matters, not the box.

    When should I see an allergist instead of managing it myself?

    See one if symptoms persist after two to three weeks of a proper daily regimen, if you rely on decongestants regularly, if allergies trigger asthma or recurrent sinus infections, or if poor sleep from congestion affects your daily life. Immunotherapy (shots or tablets) can retrain your immune response over a few years.

  • How to Lower Your A1C From 7.5 to Under 6 Without Insulin

    How to Lower Your A1C From 7.5 to Under 6 Without Insulin

    An A1C of 7.5 percent means your average blood sugar has been running around 169 mg/dL — above the target most doctors set for people with diabetes, which is under 7 percent, and well above the under-6 range you are aiming for. Getting from 7.5 to under 6 without insulin is absolutely achievable for many people with type 2 diabetes or prediabetes, but it requires understanding what A1C actually measures and pulling several levers at once: food, movement, sleep, stress, and possibly non-insulin medications. This is a months-long project, not a two-week fix — and it is worth doing right, because every point of A1C reduction meaningfully cuts your risk of complications.

    What A1C Measures (and Why It Moves Slowly)

    A1C reflects your average blood sugar over the past two to three months, based on how much glucose has attached to your red blood cells. Because red blood cells live about three months, A1C is a slow-moving number — changes you make today show up gradually, and you should retest no sooner than three months after a big lifestyle change. This is actually good news: it means the number rewards sustained habits, not perfection on any single day.

    To translate the goal: an A1C of 7.5 corresponds to an estimated average glucose of about 169 mg/dL; getting under 6 means averaging below 126 mg/dL. That is a real but very doable shift — roughly the difference between a diet and activity pattern that spikes after every meal and one that keeps post-meal rises modest. Work with your doctor on this goal, especially if you take any glucose-lowering medications, because improving your numbers can require dose adjustments to avoid low blood sugar. The National Institute of Diabetes and Digestive and Kidney Diseases offers a clear primer on what A1C means and how targets are set.

    Food: The Biggest Lever You Control

    Diet drives the majority of A1C change. The single most impactful shift is reducing the glycemic load of your meals — not necessarily eliminating carbs, but restructuring them. Start with the plate method: half the plate non-starchy vegetables, a quarter lean protein, a quarter whole-food carbs like beans, lentils, or intact whole grains. Eat the vegetables and protein first and the carbs last; studies show meal sequencing alone can cut the post-meal glucose spike significantly.

    Cut the biggest offenders ruthlessly: sugary drinks (soda, sweet tea, juice, fancy coffee drinks) are the fastest way to spike blood sugar and the easiest win — replacing them with water, unsweetened tea, or black coffee can drop A1C on its own. Then address refined starches: white bread, pastries, white rice, and sugary cereals. You do not need keto; you need fewer rapid-digesting carbs and more fiber. Aim for 25 to 35 grams of fiber daily from vegetables, legumes, nuts, and whole grains — fiber slows glucose absorption and improves insulin sensitivity. Time-restricted eating (for example, finishing dinner by 7PM and eating breakfast at 8AM) helps some people by reducing late-night snacking, but keep it moderate and discuss it with your doctor if you take diabetes medications.

    Movement: The Insulin-Free Glucose Disposal System

    Exercise lowers blood sugar through a pathway that does not require insulin at all: contracting muscles pull glucose directly from the blood. A brisk 20- to 30-minute walk after meals is one of the most powerful tools available — post-meal walks blunt the glucose spike from the food you just ate, and the effect is immediate and measurable. If you do nothing else, walk after your two biggest meals daily.

    For the bigger A1C shift, add resistance training two to three times a week. Muscle is your largest glucose sink, and building more of it improves insulin sensitivity around the clock, not just during the workout. Bodyweight exercises, resistance bands, or light dumbbells all work — the research shows meaningful A1C improvements from resistance training even without weight loss. Combine that with 150 minutes weekly of moderate aerobic activity (brisk walking, cycling, swimming), and you have the exercise prescription every diabetes guideline recommends. The American Diabetes Association’s standards of care detail exactly how activity improves glycemic control.

    Sleep, Stress, and the Hidden Drivers

    Two underrated levers: sleep and stress. Sleeping less than seven hours impairs insulin sensitivity the next day — one bad night can measurably raise your glucose. Sleep apnea, common in people with type 2 diabetes, fragments sleep and drives insulin resistance; if you snore heavily or wake unrefreshed, get evaluated. Chronic stress raises cortisol, which raises blood sugar directly; daily stress management — walking, breathing exercises, or whatever genuinely calms you — is not wellness fluff but glucose control.

    Weight loss amplifies everything: losing 5 to 10 percent of body weight can improve insulin sensitivity dramatically, and for some people with type 2 diabetes, larger losses can put the condition into remission. But do not make weight loss the gatekeeper — the food, movement, sleep, and stress changes lower A1C even before the scale moves much. Track with a glucose meter or continuous glucose monitor if your doctor recommends one; seeing your personal response to specific foods is the fastest education available.

    Non-Insulin Medications: A Legitimate Part of the Plan

    “Without insulin” does not have to mean “without medication.” Metformin remains the first-line drug for type 2 diabetes — it reduces liver glucose production, does not cause weight gain, and has decades of safety data. Newer classes like GLP-1 receptor agonists (semaglutide and similar) lower A1C substantially while often producing significant weight loss, and SGLT2 inhibitors lower glucose through the kidneys while protecting the heart and kidneys. Many people reach an A1C under 6 with lifestyle changes plus one of these — no insulin required.

    The key point: needing medication is not failure. Type 2 diabetes is a progressive condition for many people, and combining lifestyle change with the right non-insulin medication often achieves what lifestyle alone cannot. What matters is the result — an A1C under 6 with minimal side effects — not the purity of the method. Have an honest conversation with your doctor about which options fit your situation, costs, and preferences.

    Moving A1C from 7.5 to under 6 without insulin means averaging blood sugar below 126 mg/dL instead of 169 — achievable through cutting sugary drinks and refined carbs, walking after meals, resistance training twice weekly, 7+ hours of sleep, and stress management, with non-insulin medications like metformin or GLP-1 drugs as legitimate accelerators. Retest after three months of consistent change.

    Conclusion

    Lowering your A1C from 7.5 to under 6 without insulin is a realistic goal built from unglamorous daily actions: restructure your plate, eliminate sugary drinks, walk after meals, lift weights twice a week, sleep seven-plus hours, and manage stress. Add a non-insulin medication if your doctor recommends it — that is smart strategy, not defeat. Give it three full months before judging, track your numbers, and adjust with your doctor as your glucose improves. Every fraction of a point you bring down is real risk reduction for your eyes, kidneys, nerves, and heart. For more metabolic health coverage, explore our health articles, read about our editorial approach, or share your own blood sugar journey.

    Frequently Asked Questions

    How long does it take to lower A1C from 7.5 to under 6?

    A1C reflects three months of average blood sugar, so expect three to six months of consistent lifestyle change to see the full shift. Some people see meaningful movement at the three-month retest; others need six months, especially if medication adjustments are part of the plan.

    Can diet alone bring my A1C under 6, or do I need medication?

    It depends on your individual physiology, but many people with an A1C of 7.5 reach under 6 with diet, exercise, sleep, and stress changes alone. Others need a non-insulin medication like metformin or a GLP-1 drug to get there. Needing medication is not failure — the goal is the number, not the method.

    What foods should I cut first to lower blood sugar?

    Start with sugary drinks — soda, sweet tea, juice, sugary coffee drinks — the fastest spikes and the easiest elimination. Then reduce refined starches: white bread, pastries, white rice, sugary cereals. Replace them with vegetables, legumes, nuts, lean protein, and intact whole grains, aiming for 25 to 35 grams of fiber daily.

    Does walking really lower blood sugar?

    Yes, measurably. Contracting muscles pull glucose from the blood without needing insulin, so a brisk 20- to 30-minute walk after meals directly blunts the post-meal spike. It is one of the most evidence-backed, lowest-cost glucose interventions available.

    Will losing weight lower my A1C even if I do not reach my goal weight?

    Yes. Losing just 5 to 10 percent of body weight meaningfully improves insulin sensitivity and A1C. Larger losses can sometimes put type 2 diabetes into remission, but do not wait for a big number on the scale — the lifestyle changes lower glucose well before major weight loss.

    Is it safe to try for an A1C under 6?

    For most people with type 2 diabetes or prediabetes, yes — but discuss the target with your doctor, especially if you take glucose-lowering medications, because improving numbers can require dose reductions to avoid hypoglycemia. Your doctor may set a slightly different target based on your age, other conditions, and hypoglycemia risk.

  • Why Your Back Hurts More on Days You Skip Exercise

    Why Your Back Hurts More on Days You Skip Exercise

    You skip your workout, spend the day at your desk or on the couch, and by evening your back is aching in a way it never does on gym days. It feels backwards — should rest not help a sore back? Yet the pattern is unmistakable: move, feel fine; sit all day, hurt. This is one of the most common experiences in adult life, and it has a clear physiological explanation. Your back does not hurt despite the rest — it hurts because of it.

    Your Spine Is Built to Move, Not to Sit

    The structures in your back — spinal discs, facet joints, ligaments, and the deep stabilizing muscles — are designed for regular motion. Spinal discs have no direct blood supply; they receive nutrients through a process called imbibition, where movement literally pumps fluid in and out of the disc like squeezing a sponge. Sit still for eight hours and that pumping stops. The discs dehydrate slightly, the surrounding tissues stiffen, and the small joints of the spine get cranky from being locked in one position.

    Meanwhile, your muscles respond to stillness by tightening up. The hip flexors shorten in a seated position, tilting the pelvis and increasing the arch in your lower back. The glutes — your body’s biggest stabilizers — essentially go to sleep, a phenomenon trainers call “gluteal amnesia,” leaving the lower back muscles to do work they were not designed for alone. On exercise days, you reverse all of this: movement rehydrates discs, wakes up the glutes, stretches the hip flexors, and flushes the tissues. That is why the workout does not just distract from the ache — it treats the cause. The Mayo Clinic’s back pain guide emphasizes that staying active, not resting, is the cornerstone of managing most back pain.

    The Inflammation Connection

    There is a second, subtler mechanism: movement is anti-inflammatory. Regular physical activity triggers the release of anti-inflammatory compounds and improves circulation, which clears inflammatory byproducts from tissues. On sedentary days, low-grade inflammation accumulates — particularly if you are also sleeping poorly, stressed, or eating inflammatory foods, all of which cluster on lazy days. People with chronic back issues often notice their pain follows their activity level with a 12- to 24-hour delay, which is why the skipped workout punishes you the next day rather than immediately.

    This also explains why the pain often feels worse in the morning after a sedentary day: overnight stillness compounds the daytime stillness, and you wake up stiff. Gentle morning movement — even five minutes of walking, cat-cow stretches, or simply not sitting for the first hour — can break the cycle before it sets in. The goal is not intensity; it is interrupting prolonged stillness.

    Why “Resting Your Back” Is Mostly a Myth

    For decades, the standard advice for back pain was bed rest. Modern medicine has reversed that completely: for the vast majority of back pain — the mechanical, non-specific kind that most of us get — prolonged rest makes things worse, not better. Bed rest beyond a day or two leads to muscle deconditioning, stiffer joints, and a longer recovery. Every major clinical guideline now recommends staying as active as tolerable and returning to normal movement quickly.

    The exceptions are real but narrow: a fresh injury with severe pain, numbness or weakness in the legs, loss of bladder or bowel control, or pain after significant trauma all warrant medical evaluation and possibly rest. But the familiar dull ache after a day of sitting is not one of them. If your back hurts more on rest days, that is your body telling you the rest is the problem, delivered in the only language it has. The National Institute of Arthritis and Musculoskeletal and Skin Diseases provides an evidence-based overview of when back pain needs medical attention versus movement.

    What to Do on Days You Cannot Work Out

    You do not need a full workout to keep your back happy — you need to break up stillness. The research-backed target is to avoid sitting for more than 30 to 60 minutes at a stretch. Set a timer and stand, walk to get water, or do 60 seconds of movement: bodyweight squats, a doorway chest stretch, walking lunges down the hall. These micro-breaks are surprisingly powerful because they restart the disc-pumping and muscle-activation processes.

    A short mobility routine takes ten minutes and covers the essentials: cat-cow for spinal motion, child’s pose for the lower back, a kneeling hip flexor stretch for the tight fronts of the hips, glute bridges to wake up the posterior chain, and dead hangs or a simple standing back extension. Do it once in the morning and once in the evening on rest days, and most people find the sedentary-day ache largely disappears. Walking counts enormously — a 20-minute walk is legitimate back therapy, not a consolation prize.

    Building a Back That Does Not Punish Rest Days

    The long-term fix is a stronger, more resilient posterior chain. The muscles that protect your spine are the glutes, the deep core (transverse abdominis and multifidus), and the back extensors. Two to three sessions a week of deadlifts or hip hinges (even light kettlebell work), rows, and core stability exercises like bird-dogs and side planks build a back that tolerates a lazy Sunday without complaint. This is not about having an athlete’s body — it is about having enough baseline strength that one sedentary day does not drop you below the pain threshold.

    Also audit your sitting setup, since you will still sit plenty. Hips slightly above knees, feet flat, lumbar support maintaining the lower back’s natural curve, screen at eye level, and — most importantly — a setup you actually change positions in. The best posture is your next posture. A standing desk you never raise is just an expensive regular desk; the value is in the switching.

    Your back hurts more on rest days because spinal discs need movement to stay hydrated, sitting tightens hip flexors and deactivates glutes, and stillness lets low-grade inflammation accumulate. The fix is not more rest — it is breaking up sitting every 30 to 60 minutes and building posterior-chain strength two to three times a week.

    Conclusion

    The rest-day backache is your body’s honest feedback: it was designed to move, and a day of stillness has real physiological costs — dehydrated discs, sleepy glutes, tight hip flexors, and pooled inflammation. You do not need to train hard every day to fix it; you need to stop sitting for hours uninterrupted, add a ten-minute mobility routine on off days, and build baseline strength over time. Respect the red flags that need a doctor, but for the ordinary ache, the prescription is motion. For more musculoskeletal health coverage, visit our health section, learn about our editorial standards, or share what works for your back.

    Frequently Asked Questions

    Why does my back hurt more the day after I skip exercise?

    Spinal discs rehydrate through movement, and without it they stiffen; hip flexors tighten from sitting while glutes deactivate, shifting load onto the lower back; and low-grade inflammation accumulates without activity’s anti-inflammatory effect. The pain often lags 12 to 24 hours behind the sedentary day.

    Is it bad to rest when my back hurts?

    For ordinary mechanical back pain, prolonged rest makes things worse — it deconditions muscles and stiffens joints. Stay as active as you comfortably can and return to normal movement quickly. Rest is only appropriate for severe fresh injuries or red-flag symptoms like leg numbness, weakness, or loss of bladder control, which need medical evaluation.

    What is the fastest way to relieve back pain from sitting all day?

    Get moving: a 20-minute walk, cat-cow stretches, child’s pose, a kneeling hip flexor stretch, and glute bridges. Heat can relax tight muscles. The key is sustained gentle motion rather than one stretch — aim to keep moving and avoid sitting back down for another long stretch.

    How often should I get up from my desk to protect my back?

    Avoid sitting for more than 30 to 60 minutes continuously. Set a timer, stand up, walk briefly, or do 60 seconds of movement each hour. Frequent short breaks outperform one long break, because they keep restarting the processes that keep spinal tissues healthy.

    What exercises build a back that tolerates rest days?

    Focus on the posterior chain two to three times weekly: hip hinges or light deadlifts, rows, glute bridges, bird-dogs, and side planks for deep core stability. You do not need heavy weights — consistent moderate work builds the baseline resilience that prevents one sedentary day from causing pain.

    When should back pain send me to a doctor?

    See a doctor for pain after significant trauma, numbness or weakness in the legs, loss of bladder or bowel control, fever with back pain, unexplained weight loss, or pain that does not improve after a few weeks of staying active. These can indicate conditions beyond ordinary mechanical back pain.

  • Has Your Mole Changed Enough to See a Dermatologist?

    Has Your Mole Changed Enough to See a Dermatologist?

    Most of us have moles we have lived with for years — that familiar spot on the shoulder, the one on the calf you barely notice anymore. Then one day you catch it in the mirror and something looks… different. Bigger? Darker? Was that edge always that uneven? The anxiety that follows is real, and so is the uncertainty: is this worth a dermatologist appointment, or am I overreacting? Dermatologists hear this question constantly, and there is a clear, practical framework for answering it. Most changed moles turn out to be harmless, but the ones that are not caught early are exactly the ones where early action saves lives.

    The ABCDE Rule: What Dermatologists Actually Look For

    The standard screening tool is the ABCDE rule, and it is worth memorizing because it turns vague worry into a concrete checklist. A stands for Asymmetry: draw an imaginary line through the mole — do the two halves look different? B is Border: are the edges irregular, blurred, or jagged rather than smooth and even? C is Color: is the color varied — different shades of brown, black, tan, red, white, or blue — instead of one uniform tone? D is Diameter: is it larger than about 6 millimeters, roughly the size of a pencil eraser? E is Evolution: has it changed in size, shape, color, elevation, or symptoms like itching, crusting, or bleeding?

    Evolution is the most important letter. A mole that has always been asymmetrical and multicolored is usually just your mole; a mole that is changing is the one that deserves attention. Dermatologists take the E especially seriously because melanoma — the dangerous skin cancer — almost always announces itself through change. The American Academy of Dermatology’s guide to spotting skin cancer walks through each sign with visual examples worth reviewing before your appointment.

    The “Ugly Duckling” Sign: Your Best Personal Tool

    Beyond ABCDE, dermatologists use a concept called the “ugly duckling” sign: the mole that looks different from all your other moles. Most people have a personal mole pattern — if all your moles are small and brown, and one is large, dark, and irregular, that outlier deserves a look regardless of whether it checks every ABCDE box. This is especially useful because some melanomas do not follow the classic rules; they can be small, uniformly colored, or otherwise sneaky.

    This is also why baseline familiarity matters. Once or twice a year, do a head-to-toe self-exam in good light with a hand mirror for hard-to-see areas: scalp, ears, back of the neck, between the toes, under the nails, and the soles of the feet. Melanoma can appear in places that never see the sun. Take phone photos of moles that concern you, with a coin or ruler for scale — a dated photo series is enormously helpful to a dermatologist, because it documents change objectively instead of relying on memory.

    Changes That Are Usually Harmless (But Still Worth Knowing)

    Not every change is sinister. Moles can darken during pregnancy due to hormonal shifts, and new moles can appear during the teen years and twenties. Moles often become raised, flesh-colored, or develop little hairs over decades — typically benign evolution. Skin tags and seborrheic keratoses (waxy, stuck-on-looking growths) multiply with age and look alarming but are harmless. Irritation from clothing, shaving, or scratching can make a mole temporarily red, swollen, or scabbed.

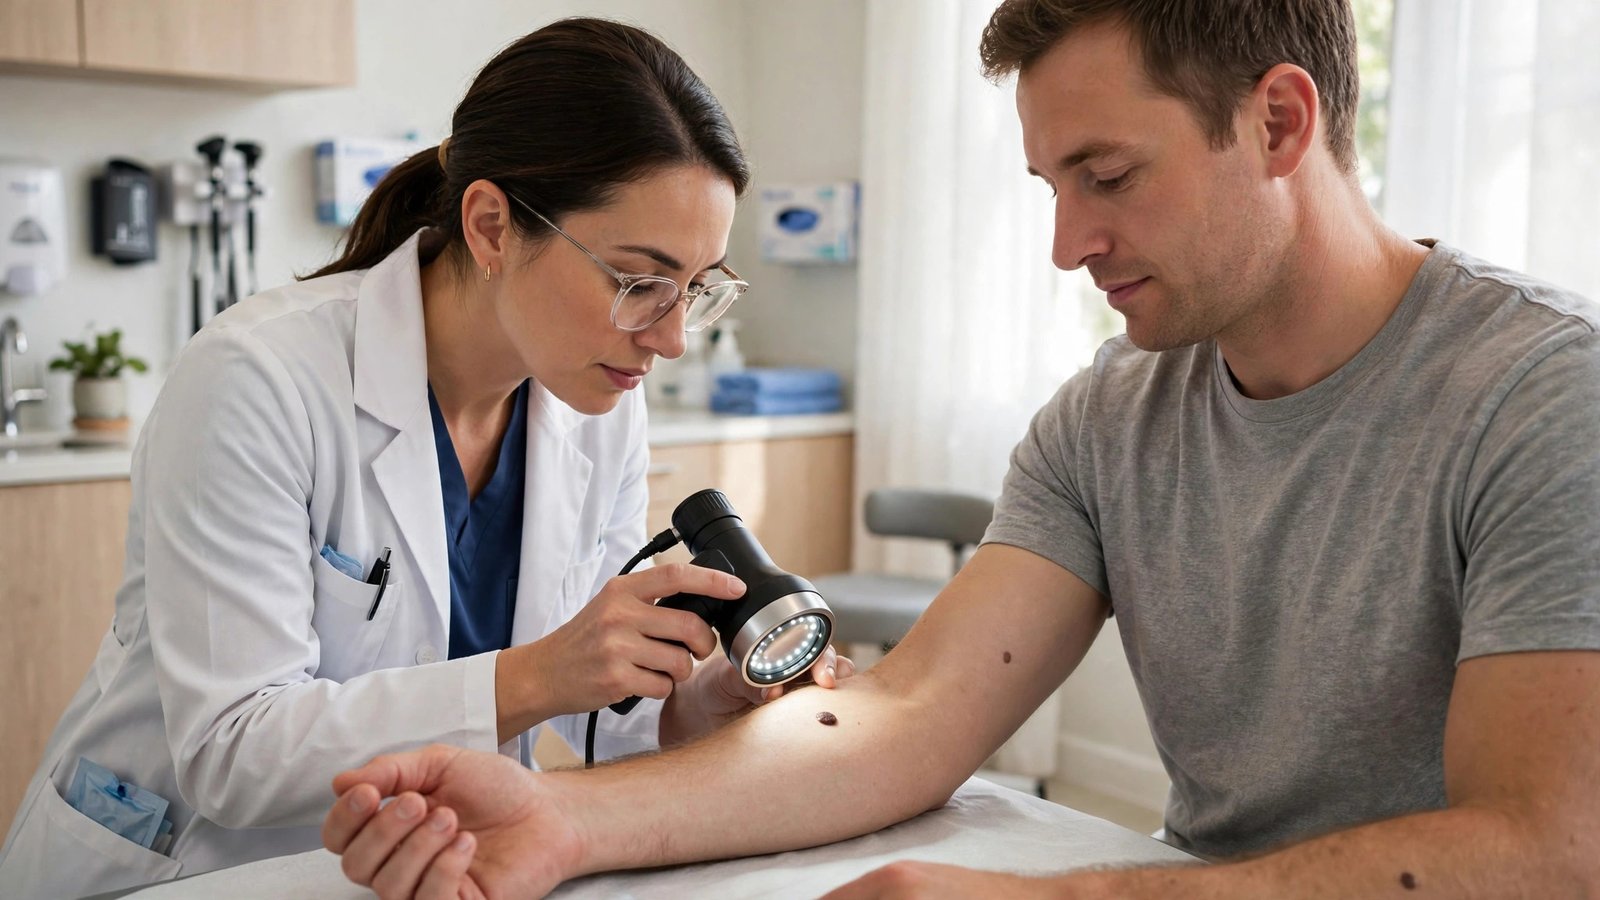
    The key distinction is persistence and trajectory. A mole that got irritated by a backpack strap and calmed down in a week is a different story from a mole that keeps growing, changing color, or bleeding repeatedly. When in doubt, the rule dermatologists themselves follow is simple: if a spot is changing and you cannot explain why, get it checked. A quick dermoscopy — the dermatologist looks through a handheld magnifier — takes minutes and resolves most worries on the spot.

    What Happens at the Dermatologist Appointment

    Knowing what to expect removes a lot of the dread. The dermatologist will ask about the spot’s history and your sun exposure and family history, then examine it with a dermatoscope, a handheld device that magnifies the skin’s structures far beyond what the naked eye sees. Most concerning-but-benign spots are diagnosed right there, no procedure needed. If the spot looks genuinely suspicious, the next step is a biopsy — usually a small shave or punch sample taken under local anesthetic in the office, taking about ten minutes.

    Do not let fear of the biopsy stop you from going. The procedure is minor — a numbing injection, a tiny sample, sometimes a stitch or two — and it is the only way to know for certain. Catching melanoma early is the entire ballgame: the American Cancer Society’s melanoma statistics show that five-year survival for localized melanoma caught early exceeds 99 percent, while late-stage detection drops dramatically. The appointment you are nervous about is precisely what makes the outcome boring instead of frightening.

    Who Should Be Extra Vigilant

    Some people should have a lower threshold for getting checked. Risk factors include fair skin that burns easily, a history of blistering sunburns (especially in childhood), lots of moles (more than 50), atypical or large moles, a personal or family history of skin cancer or melanoma, and immune suppression. If melanoma runs in your family, ask your relatives about genetic counseling and consider a baseline full-body skin exam with a dermatologist even without a specific concerning spot.

    For everyone else, the practical cadence is: monthly-ish self-awareness (you do not need a formal ritual — just notice your skin), a careful self-exam once or twice a year, and a dermatologist visit for anything that is changing without explanation, plus an annual professional skin check if you are high-risk. Sun protection remains the best prevention: broad-spectrum SPF 30+, reapplied every two hours outdoors, protective clothing, and shade during peak hours. Your future self will thank you.

    A mole that is changing — in size, shape, color, or symptoms — deserves a dermatologist visit, even if it does not check every ABCDE box. Photograph it with a coin for scale, note when you first noticed the change, and book the appointment without guilt. Early-detected melanoma has a survival rate above 99 percent; the check itself takes minutes.

    Conclusion

    Deciding whether a changed mole warrants a dermatologist comes down to one principle: unexplained change gets checked. Use the ABCDE rule and the ugly duckling sign as your guides, document with dated photos, and do not talk yourself out of the appointment — dermatologists would far rather reassure you about a benign spot than meet you six months later. Most changed moles are harmless, and the visit is quick and painless. The small effort of getting checked is the entire difference between a scare and a tragedy. For more health guidance, browse our health section, read about our editorial approach to medical topics, or send us your health questions.

    Frequently Asked Questions

    What does the ABCDE rule stand for in mole checking?

    Asymmetry (halves look different), Border (irregular or blurred edges), Color (varied shades instead of uniform), Diameter (larger than about 6mm, a pencil eraser), and Evolution (any change in size, shape, color, or symptoms). Evolution — change itself — is considered the most important sign.

    My mole has always looked weird. Should I still get it checked?

    A mole that has always been unusual but stable is usually just your normal. What matters is change: if it starts growing, changing color, itching, crusting, or bleeding, get it evaluated. When in doubt, a dermatologist can establish a baseline with dermoscopy and monitor it.

    What is the “ugly duckling” sign?

    It is the mole that looks different from all your other moles. If most of your moles are small and brown and one is large, dark, and irregular, that outlier deserves examination even if it does not meet every ABCDE criterion. It is one of the most useful self-screening concepts dermatologists teach.

    Does a skin biopsy hurt?

    Very little. The area is numbed with a local anesthetic injection (a brief sting), and the sample itself — usually a shave or small punch — takes minutes and is painless. Most biopsies need no stitches or just one or two, and results typically come back within a week or two.

    Can moles change during pregnancy?

    Yes. Hormonal shifts in pregnancy can darken existing moles and cause new ones to appear. Most of these changes are benign, but because pregnancy can also mask concerning changes, dermatologists advise getting any rapidly changing, bleeding, or highly irregular mole checked promptly during pregnancy too.

    How often should I do a skin self-exam?

    A careful head-to-toe self-exam once or twice a year is a good cadence for most people, plus general awareness month to month. High-risk individuals — fair skin, many moles, family history of melanoma — should ask their dermatologist about annual professional full-body exams.

  • What to Do If Your Child Swallows a Small Coin

    What to Do If Your Child Swallows a Small Coin

    It happens in a split second: you turn around, and your toddler is chewing on something shiny. A penny. A dime. Gone. Your heart pounds, and your mind races through worst-case scenarios. Here is the reassuring truth first: in the vast majority of cases, a swallowed coin passes through a child’s digestive system on its own within a few days, without any intervention. But “usually fine” is not the same as “always fine,” and there are specific situations where a swallowed coin is a genuine emergency. Knowing the difference — what to do, what not to do, and when to call for help — turns panic into a plan.

    First Things First: Stay Calm and Assess

    Your reaction sets the tone. If your child is breathing normally, not coughing or choking, talking or crying normally, and not in obvious pain, the coin almost certainly went down the esophagus into the stomach rather than the airway — and that is the far better scenario. An object in the airway causes immediate distress: inability to breathe, high-pitched noisy breathing, or a panicked silent struggle. That is a 911 situation. A coin that went to the stomach, by contrast, is something to manage thoughtfully, not frantically.

    Try to determine what was swallowed and when. A US penny is about 19 millimeters across; a dime is smaller at 18 millimeters; a quarter is 24 millimeters. Smaller coins pass more easily, and size matters to the doctors if you end up calling. Note the time — it helps medical providers judge how far along the coin might be. If you are not sure it was actually swallowed (versus hidden somewhere), check the mouth, and if there is any doubt about breathing, treat it as an emergency first and sort out the details later.

    Call Your Pediatrician or Poison Control — Yes, Really

    Even when your child seems perfectly fine, call your pediatrician’s office or Poison Control at 1-800-222-1222 for guidance. This is not overreacting; it is exactly what these services are for, and they handle swallowed-object calls constantly. They will ask about the child’s age, the coin’s size and type, the time of swallowing, and current symptoms, then tell you whether to watch at home or come in. The American Academy of Pediatrics’ guidance on swallowed objects similarly advises contacting your pediatrician for direction rather than guessing.

    There is one coin-related exception that changes everything: button batteries. If there is any chance your child swallowed a button or coin-cell battery instead of (or along with) a coin — from a remote, a musical greeting card, a flameless candle — that is an immediate emergency. Button batteries can burn through the esophagus in as little as two hours. Go to the emergency room at once; do not wait for symptoms. If you are certain it was a regular coin, the urgency is much lower, but the call is still worth making.

    Go to the ER Immediately If You See These Signs

    Certain symptoms mean the coin may be stuck in the esophagus, and a stuck coin needs prompt medical attention. Head to the emergency room if your child is drooling excessively or cannot swallow saliva, refuses to eat or drink, complains of pain in the throat, chest, or neck, is vomiting repeatedly, has noisy or difficult breathing, or develops a fever. These suggest the coin is lodged rather than moving through — most commonly at one of the esophagus’s natural narrow points.

    Timing matters too. If your child swallowed the coin more than 24 hours ago and you have seen no sign of it passing, or if symptoms develop or worsen at any point, get evaluated. In the ER, doctors will typically take an X-ray to locate the coin — coins show up clearly on X-ray, which is why metal objects are in some ways easier to manage than swallowed plastic. A coin lodged in the esophagus is usually removed with an endoscope, a quick procedure done under sedation. The Mayo Clinic’s overview of swallowed foreign objects explains when observation is enough and when removal is needed.

    What NOT to Do (Common Mistakes)

    Do not try to make your child vomit. Vomiting will not reliably bring up a coin, and it risks moving the coin into the airway on the way back up — turning a stomach problem into a breathing emergency. Do not perform the Heimlich maneuver or back blows on a child who is breathing fine; those are for choking, not for something already swallowed. Do not feed your child large amounts of bread, bananas, or other food to “push it down” — this is an old folk remedy with no evidence behind it, and it can complicate things if the coin is lodged.

    Do not stick your fingers down your child’s throat to fish for the coin either. You cannot see what you are doing, you risk pushing it deeper or triggering vomiting, and a scared, gagging child is harder to assess. The correct approach for an asymptomatic child is boring on purpose: confirm the child is comfortable, call for medical guidance, and monitor. Restraint feels wrong when you are scared, but it is genuinely the safest move.

    Watching and Waiting: What the Next Few Days Look Like

    If your pediatrician advises home observation, the coin will typically pass in the stool within two to five days, though it can occasionally take up to a week or more. You do not need to dig through every diaper or bowel movement — but many parents do a quick check, and that is fine. Keep your child’s diet and activity normal; there is no special diet that speeds things along, though staying hydrated and eating fiber-rich foods keeps everything moving normally.

    Watch for warning signs during the waiting period: abdominal pain, vomiting, blood in the stool, black or tarry stools, fever, or refusal to eat. Any of these warrant a prompt call to your pediatrician or a trip to urgent care. Also note that older pennies (minted before 1982) are mostly copper, while newer ones are zinc with copper plating — zinc can be irritating in large amounts, but a single penny is not a zinc toxicity concern. One coin, one time, in a healthy child: the odds are overwhelmingly in your favor.

    If your child swallows a small coin and is breathing normally with no pain, stay calm, call your pediatrician or Poison Control for guidance, and do not induce vomiting or try to fish it out. Go to the ER for drooling, trouble swallowing, chest or throat pain, vomiting, or breathing difficulty. Most coins pass on their own within a few days.

    Conclusion

    A swallowed coin is one of the most common childhood scares, and it resolves uneventfully the vast majority of the time. The playbook is simple: confirm your child is breathing comfortably, call your pediatrician or Poison Control at 1-800-222-1222, avoid the urge to intervene physically, and monitor over the next few days. Know the red flags that mean the ER — drooling, inability to swallow, pain, vomiting, breathing trouble — and treat any possible button battery as an immediate emergency. Then childproof with fresh eyes so the next shiny object never makes it to little hands. For more family health guidance, explore our health articles, learn about who we are, or share your own parenting scare stories.

    Frequently Asked Questions

    How long does it take for a swallowed coin to pass?

    Most coins pass through the digestive system and appear in the stool within two to five days, though it can occasionally take a week or longer. Keep your child’s diet and activity normal, and contact your pediatrician if a week passes with no sign of it or if any symptoms develop.

    Should I make my child throw up after swallowing a coin?

    No. Do not induce vomiting — it will not reliably bring the coin up and risks moving it into the airway, turning a stomach issue into a breathing emergency. The same goes for the Heimlich maneuver on a child who is breathing fine; that is for choking, not for swallowed objects.

    When does a swallowed coin require an emergency room visit?

    Go to the ER if your child drools excessively, cannot swallow, complains of throat, chest, or neck pain, vomits repeatedly, has trouble breathing, or develops a fever. Also go if there is any chance a button battery was swallowed instead of a coin — that is an immediate emergency regardless of symptoms.

    Will the coin show up on an X-ray?

    Yes. Coins are metal and show up clearly on X-ray, which is why doctors can quickly locate them and determine whether the coin is in the esophagus (where it may need removal) or already in the stomach or intestines (where it will usually pass on its own).

    Do I need to check my child’s stool for the coin?

    You do not have to, but many parents do a quick check for peace of mind. What matters more is watching for warning signs during the waiting period: abdominal pain, vomiting, blood in the stool, black stools, fever, or refusal to eat. Any of those warrant a call to your pediatrician.

    Are pennies dangerous because of the zinc?

    A single penny is not a zinc toxicity concern. Pennies minted before 1982 are mostly copper; newer ones are zinc with copper plating. Zinc can be irritating in large quantities, but one swallowed coin in a healthy child does not pose a heavy-metal risk — the concern with coins is mechanical (getting stuck), not chemical.

  • How to Safely Remove a Tick From Your Dog’s Ear After a Hike

    How to Safely Remove a Tick From Your Dog’s Ear After a Hike

    You get home from a great hike, your dog is happily exhausted, and then you spot it: a small dark bump on the inside of your dog’s ear that was not there this morning. A tick. Your first instinct might be to grab it with your fingers and yank — do not. Ticks removed the wrong way can leave mouthparts embedded, squeeze bacteria into the bite, or stress a dog into snapping. Removing a tick from a dog’s ear is straightforward and safe if you do it methodically, and the ear location adds a few specific considerations worth knowing before you start.

    Before You Touch the Tick: What to Gather

    You need four things: fine-tipped tweezers (not the blunt household kind — pointed precision tweezers grip the tick’s head without crushing its body), disposable gloves, rubbing alcohol or an antiseptic wipe, and a small sealed container or jar with a bit of rubbing alcohol in it for the tick. If you do not have fine-tipped tweezers, a purpose-made tick removal tool works well and costs a few dollars at any pet store; keep one in your hiking kit going forward.

    Set yourself up in good light — the ear is shadowed, and you need to see exactly what you are gripping. Have a helper hold and calm your dog if possible; ear work makes many dogs head-shy, and a second pair of hands prevents sudden head shakes at the worst moment. Offer a high-value treat or a lick mat with peanut butter to keep your dog still and associate the process with good things. If your dog is in pain, snapping, or will not let you near the ear, stop and call your vet — a struggling dog plus tweezers near the ear canal is a bad combination.

    Step-by-Step: Removing the Tick from the Ear

    First, part the fur and get a clear look. Ticks on the ear are usually on the inner flap (the pinna) or around the base of the ear — if it is deep inside the ear canal where you cannot see the attachment point clearly, do not dig for it; that is a vet visit. Put on your gloves. With the fine-tipped tweezers, grasp the tick as close to your dog’s skin as possible — you want the head and mouthparts, not the swollen body. This is the most important part of the entire process.

    Pull straight outward with steady, even pressure. Do not twist, jerk, or yank — twisting can break off the mouthparts, and jerking startles the dog. Drop the tick into your jar of rubbing alcohol, which kills it and preserves it for identification if your dog develops symptoms later. Then clean the bite area on the ear with rubbing alcohol or an antiseptic wipe, and wash your hands thoroughly even though you wore gloves.

    What not to do matters as much as what to do. Never burn the tick with a match, smother it with nail polish or petroleum jelly, or crush it with your fingers — all the folk remedies either fail or increase the risk of the tick regurgitating bacteria into the bite. The CDC’s tick removal guidance is explicit: fine-tipped tweezers, steady pull, clean the area. No shortcuts.

    Ear-Specific Concerns Worth Knowing

    The ear flap has thin skin with a rich blood supply, which is exactly why ticks love it — but it also means the area bleeds more freely than you might expect and can bruise. A little bleeding after removal is normal; apply gentle pressure with clean gauze for a minute or two. The ear is also sensitive, so expect your dog to flinch — work calmly and quickly, and keep sessions short. If the tick was attached for a long time, the ear tissue around it may be red and swollen for a day or two; watch that it improves rather than worsens.

    Ticks on the ear can sometimes trigger a small local reaction that looks alarming — a firm little lump at the bite site that persists for a week or more. This is usually a granuloma, a harmless inflammatory response to leftover tick saliva, and it typically resolves on its own. But a lump that grows, oozes, or is hot to the touch needs a vet’s eyes. Also note: the same hike that put one tick on your dog’s ear probably put others elsewhere. Do a full-body check after every hike — between the toes, under the collar, in the armpits and groin, and around the tail base are the classic hiding spots.

    After Removal: What to Watch For Over the Next Weeks

    Most tick bites cause nothing more than brief local irritation. But ticks can transmit serious diseases — Lyme disease, ehrlichiosis, anaplasmosis, and Rocky Mountain spotted fever among them — and symptoms can take days to weeks to appear. Watch for lethargy, loss of appetite, fever, shifting leg lameness, swollen joints, or unusual bleeding. Lyme disease in particular can show up as intermittent limping that moves from leg to leg. The American Veterinary Medical Association’s tick disease resources describe the warning signs in detail.

    Save the tick in its alcohol jar, labeled with the date and where you were hiking, for at least a month. If your dog gets sick, the vet can identify the species, which narrows down which diseases to test for — different ticks carry different pathogens, and knowing the species genuinely helps. Your vet may recommend a tick-borne disease blood test four to six weeks after the bite, since antibodies take time to develop; a test done the day after the bite will miss an infection. This is also the moment to ask about the Lyme vaccine if you hike in tick-heavy areas regularly.

    Preventing the Next One: Post-Hike Tick Strategy

    Removal is damage control; prevention is the real game. Talk to your vet about a tick preventive that fits your region and hiking habits — options include monthly oral chews, topical treatments, and tick collars, each with different coverage and considerations. No product is 100 percent, which is why the post-hike routine matters: check your dog within a couple of hours of getting home, because ticks that have not attached yet are easy to brush off, and attached ticks transmit more disease the longer they feed.

    Remove an ear tick with fine-tipped tweezers, gripping as close to the skin as possible and pulling straight out with steady pressure — no twisting, burning, or folk remedies. Save the tick in rubbing alcohol labeled with the date, watch your dog for lethargy or limping over the next few weeks, and set up a vet-approved tick preventive plus a post-hike check routine.

    Conclusion

    Finding a tick on your dog’s ear after a hike is unsettling, but it is a solvable problem, not an emergency — as long as you remove it correctly. Fine-tipped tweezers, a steady straight pull, antiseptic cleanup, and saving the tick for identification cover the immediate job. The longer game is monitoring for symptoms over the following weeks and building a prevention routine with your vet so the next hike ends with just tired legs and a happy dog. Quick, calm, methodical — that is the whole technique. For more pet health guidance, browse our health section, learn about our editorial standards, or tell us your own post-hike tick stories.

    Frequently Asked Questions

    What if the tick’s head breaks off in my dog’s ear?

    Try once more with the tweezers to grasp the remaining mouthparts. If you cannot get them, do not dig — clean the area and let the skin heal; the body usually expels small fragments on its own. See your vet if redness, swelling, or discharge develops, which can signal infection.

    Should I twist the tick when pulling it out?

    No. Pull straight outward with steady, even pressure. Twisting can snap off the mouthparts and leave them embedded in the skin, and jerking risks startling your dog into a sudden head movement. Constant gentle tension releases the tick’s grip within seconds.

    How long does a tick need to be attached to transmit disease?

    It varies by pathogen, but for Lyme disease the tick generally needs to feed for 36 to 48 hours before transmission becomes likely. That is why prompt removal matters so much — a tick found and removed the same day as the hike is far less risky than one discovered days later.

    My dog will not let me near its ear. What should I do?

    Do not force it. A stressed, snapping dog plus tweezers near the ear canal risks injury to both of you. Call your vet — they remove ticks routinely, can sedate lightly if needed, and can check for additional ticks and discuss preventive treatment in the same visit.

    Is a lump at the bite site normal after tick removal?

    A small firm lump that appears in the days after removal is often a harmless granuloma — an inflammatory reaction to tick saliva — and it usually fades within a week or two. See your vet if the lump grows, feels hot, oozes, or your dog shows signs of illness.

    When should my dog get a tick-borne disease test after a bite?

    Wait four to six weeks after the bite, since antibodies take time to develop — testing immediately after removal will miss a new infection. Save the tick with the date and location so your vet can identify the species and know which diseases to screen for.

  • How to Strengthen Your Pelvic Floor After Having a Baby

    How to Strengthen Your Pelvic Floor After Having a Baby

    After having a baby, sneezing can become a small act of bravery. Leaking urine when you laugh, cough, or lift the car seat — and that heavy, disconnected feeling in your core — are signs that your pelvic floor went through a lot and has not recovered yet. It is one of the most common postpartum issues and one of the least talked about, partly because many new moms assume it is just the price of motherhood. It is not. The pelvic floor is a group of muscles, and like any muscles, they can be retrained and strengthened — often dramatically — with the right exercises started at the right time.

    What Childbirth Actually Does to the Pelvic Floor

    Your pelvic floor is a hammock of muscles stretching from your tailbone to your pubic bone, supporting your bladder, uterus, and bowel. During pregnancy, nine months of growing weight stretches and loads these muscles; during vaginal delivery, they stretch enormously to let the baby through, and they can tear or be weakened even without visible tearing. A C-section spares the delivery stretch but not the nine months of loading, so pelvic floor issues can follow any type of birth.

    The result is often a mix of weakness and poor coordination: the muscles may be weak, they may not fire at the right moment, or they may be tight and unable to relax properly. That last one surprises people — pelvic floor dysfunction is not always weakness; sometimes the muscles are overactive and cannot release, which causes its own set of problems like pelvic pain or difficulty emptying the bladder. This is why the “just do Kegels” advice, while well-meaning, is incomplete. The American College of Obstetricians and Gynecologists recommends postpartum pelvic floor training but notes that technique and timing matter enormously.

    When to Start (and When to Wait)

    In the first days after birth, your only job is recovery — rest, and very gentle reconnection exercises like diaphragmatic breathing and light pelvic floor squeezes if they feel comfortable and your provider has not restricted you. The formal green light usually comes at your six-week postpartum checkup, where your doctor or midwife checks healing and clears you for exercise. If you had significant tearing, an episiotomy, or a complicated delivery, your timeline may be longer — follow your provider’s guidance, not a generic calendar.

    One important rule: do not push through pain. Sharp pain, increased bleeding, or a feeling of heaviness or bulging in the vagina during exercise are signals to stop and talk to your provider. These can indicate a pelvic organ prolapse, where weakened support lets an organ press into the vaginal wall — common, treatable, but not something to power through with random workouts. A Mayo Clinic overview of pelvic organ prolapse describes the symptoms to watch for. Starting gently and progressing is always better than starting aggressively and setting yourself back.

    Kegels Done Right: The Technique Most People Get Wrong

    A Kegel is a contraction and release of the pelvic floor muscles — the ones you would use to stop the flow of urine or hold back gas. The classic mistake is bearing down instead of lifting, which pushes the organs downward and makes things worse. The correct feeling is a squeeze and lift, as if you are picking up a marble with those muscles. Your belly, buttocks, and thighs should stay relaxed; if your stomach is visibly tensing, you are recruiting the wrong muscles.

    Here is a starter program most pelvic floor therapists recommend: contract for five seconds, release fully for five seconds, and repeat ten times. Do three sets a day. The release is as important as the squeeze — muscles that never fully relax become tight and dysfunctional. After two weeks, work toward ten-second holds. Add “quick flicks”: rapid one-second squeezes, ten in a row, to train the fast-twitch fibers that catch a sneeze. Expect to feel subtle improvement in two to three weeks and meaningful change in eight to twelve weeks.

    Beyond Kegels: The Exercises That Rebuild the Whole System

    The pelvic floor does not work alone — it is part of a pressure system with the diaphragm above and the deep core muscles around it. Rebuilding the whole system gets better results than Kegels in isolation. Start with diaphragmatic breathing: lie on your back with knees bent, inhale and feel your belly and pelvic floor gently expand, exhale and feel a natural lift. Pairing the exhale with a light Kegel teaches the muscles to work with your breath, which is how they function in real life.

    Glute bridges are the next step: lie on your back, feet flat, and lift your hips while exhaling and engaging the pelvic floor. Strong glutes support the pelvic floor from behind. As you progress, add bodyweight squats (exhale and engage on the way up), bird-dogs on hands and knees for deep core coordination, and walking — genuinely one of the best postpartum exercises, since it loads the pelvic floor rhythmically without strain. Hold off on high-impact exercise like running, jumping, or heavy lifting until you can do a brisk 30-minute walk, manage a set of bridges, and hold a ten-second Kegel without leaking or heaviness.

    When to See a Pelvic Floor Physical Therapist

    If leaking, heaviness, or pelvic pain persists beyond twelve weeks of consistent exercise, or if you cannot correctly identify and contract the muscles at all, see a pelvic floor physical therapist — this is a real specialty, and it is the gold standard for postpartum recovery. A therapist does an internal and external assessment (with your consent), identifies whether your issue is weakness, tightness, or coordination, and builds a program for your specific dysfunction. Many women who “tried Kegels and they didn’t work” were doing them wrong or had a tightness problem that Kegels made worse — a single evaluation can change everything.

    Do not wait if you notice a vaginal bulge, feel like you are sitting on something, cannot empty your bladder or bowel fully, or have pain during sex that does not improve. These are not things to accept as the new normal. Ask your OB or midwife for a referral; pelvic floor PT is increasingly covered by insurance when referred for postpartum dysfunction. It is one of the highest-value investments you can make in your body after birth.

    Your pelvic floor can be retrained after childbirth — but not with random Kegels. Learn the correct squeeze-and-lift technique, pair it with breathing and glute work, progress gradually after your six-week clearance, and see a pelvic floor physical therapist if symptoms persist past twelve weeks. Most women see real improvement within two to three months of consistent work.

    Conclusion

    Strengthening your pelvic floor after having a baby is a process, not a single exercise. Start with gentle reconnection breathing in the early weeks, get your provider’s clearance at the six-week visit, master proper Kegel technique with full releases, then rebuild the surrounding system with bridges, squats, and walking. Protect your progress with good toilet habits and smart lifting mechanics. And remember the two things that matter most: consistency over intensity, and professional help over silent suffering if it is not improving. Leaking and heaviness are common, but they are not mandatory — your body did something extraordinary, and it deserves a proper recovery plan. For more postpartum and women’s health guidance, explore our health articles, read about our editorial approach, or send us your postpartum questions.

    Frequently Asked Questions

    How soon after giving birth can I start pelvic floor exercises?

    Gentle reconnection — diaphragmatic breathing and light squeezes — can begin in the first days if comfortable and your provider has not restricted you. Structured strengthening programs typically start after your six-week postpartum checkup, once your provider confirms healing and clears you for exercise.

    How do I know if I am doing Kegels correctly?

    You should feel a squeeze and lift of the pelvic floor muscles, like stopping urine flow, while your belly, buttocks, and thighs stay relaxed. If you are bearing down, holding your breath, or tensing your stomach, you are doing them wrong. A pelvic floor physical therapist can confirm your technique in a single visit.

    How long until I stop leaking after starting exercises?

    Most women notice subtle improvement within two to three weeks of consistent daily practice and meaningful change within eight to twelve weeks. If there is no improvement after twelve weeks of proper technique, see a pelvic floor physical therapist for an individualized assessment.

    Are Kegels enough, or do I need other exercises?

    Kegels alone are incomplete. The pelvic floor works with your diaphragm, deep core, and glutes, so breathing exercises, glute bridges, squats, and walking produce better results. Some women have pelvic floor tightness rather than weakness, where Kegels alone can actually make symptoms worse.

    Can I recover my pelvic floor after a C-section?

    Yes. A C-section avoids the delivery stretch, but nine months of pregnancy still load and weaken the pelvic floor, so C-section moms benefit from the same rehabilitation program. Wait for your provider’s clearance, especially regarding abdominal exercises near the incision.

    When should I see a pelvic floor physical therapist instead of doing exercises on my own?

    See one if you cannot identify or contract the muscles, if symptoms persist past twelve weeks of consistent exercise, or if you notice a vaginal bulge, incomplete bladder emptying, or persistent pelvic pain. Ask your OB or midwife for a referral — it is the gold standard for postpartum pelvic floor recovery.

  • Why Heartburn Wakes You at 3AM: Causes and Prevention That Works

    Why Heartburn Wakes You at 3AM: Causes and Prevention That Works

    Waking up at 3 in the morning with a burning sensation rising from your stomach into your throat is one of the most miserable ways to lose sleep. Your chest aches, you might taste acid, and even sitting up does not always bring relief. Nighttime heartburn is incredibly common — surveys suggest roughly three out of four people who get heartburn regularly also get it at night — yet most people only treat the daytime version and wonder why the 3AM attacks keep coming. The good news is that nighttime heartburn has specific, well-understood causes, and preventing it is mostly about timing, food choices, and how you sleep.

    Why Heartburn Strikes in the Middle of the Night

    Heartburn happens when stomach acid flows backward into the esophagus, a condition doctors call acid reflux or gastroesophageal reflux disease (GERD) when it happens often. During the day, gravity and swallowing work in your favor — every swallow pushes acid back down, and saliva naturally neutralizes it. At night, both defenses disappear. You swallow far less while asleep, saliva production drops, and lying flat removes gravity from the equation entirely. That is why reflux that feels mild at 8PM can feel brutal at 3AM: the same acid is there, but nothing is fighting it.

    There is also a circadian angle. Research suggests stomach acid production can increase during the night, and the esophagus clears acid more slowly when you are asleep. So the middle of the night is essentially the perfect storm for reflux: more acid, less clearance, no gravity. If you are asking what causes heartburn specifically around 3AM, this triple combination is the core answer. The Mayo Clinic’s guide to GERD explains how nighttime reflux differs from daytime symptoms and why it often needs its own prevention strategy.

    The Evening Habits That Set Up a 3AM Attack

    Most 3AM heartburn was scheduled hours earlier, usually at dinner or in the evening. A large, late meal is the number one setup: your stomach takes hours to empty, and a full stomach lying flat is a recipe for upward pressure on the valve (the lower esophageal sphincter) between the stomach and esophagus. Eating within two to three hours of bed is the pattern behind most nighttime cases. If dinner is at 10PM and you sleep at 11PM, the 3AM wake-up is practically guaranteed.

    Specific foods make it worse. High-fat meals (burgers, fried food, pizza, creamy pasta) slow stomach emptying, keeping food in the stomach longer. Chocolate, peppermint, coffee, alcohol, citrus, tomato sauces, and spicy food can all relax the esophageal valve or directly irritate the esophagus. Alcohol deserves special mention: many people have a drink or two in the evening, and alcohol both relaxes the valve and stimulates acid production — then you lie down and pay for it at 3AM. Carbonated drinks add gas pressure that pushes acid upward. You do not have to give up everything you enjoy; you just need to know which items are high-risk in the evening window.

    How You Sleep Matters as Much as What You Ate

    Lying completely flat is the worst position for reflux because there is zero gravitational help. But the fix is not just “use more pillows” — propping your head on a stack of pillows bends your neck without really raising your stomach above your esophagus, and it can cause neck pain on top of the heartburn. What actually works is elevating the head of the bed itself by six to eight inches, using bed risers or a wedge-shaped pillow that raises your whole upper body. This keeps your stomach below your esophagus all night, and studies show it meaningfully reduces nighttime reflux episodes.

    Which side you sleep on matters too. The stomach sits mostly on the left side of your body, so sleeping on your left side keeps the stomach below the esophagus and the valve above the pool of acid. Sleeping on your right side does the opposite — it positions the valve below the acid line and tends to worsen reflux. This is one of the simplest, cheapest changes you can make: if you are a right-side sleeper who wakes at 3AM with heartburn, switching sides is worth a two-week trial.

    What to Do When It Hits at 3AM

    When you wake up burning, start by sitting up and staying upright for a while — gravity is your fastest ally. A glass of water helps wash acid back down and dilutes what is in the esophagus. Chewing gum (sugar-free) for about 30 minutes stimulates saliva, which is your body’s natural antacid, and research backs this up. Over-the-counter antacids like Tums or Rolaids can give quick relief by neutralizing acid on contact, though the effect is short-lived.

    For the next few nights, a nighttime H2 blocker such as famotidine (Pepcid) taken before bed can reduce acid production during sleep — many gastroenterologists recommend this specifically for nighttime symptoms. If episodes are frequent, a daily proton pump inhibitor (like omeprazole) is the standard long-term treatment, but that is a conversation to have with your doctor or pharmacist, not a 3AM self-prescription. Avoid lying back down immediately after the burning eases; give it at least 20 to 30 minutes upright.

    When Nighttime Heartburn Needs a Doctor

    Occasional nighttime heartburn is a nuisance, but certain patterns are medical red flags. See your doctor if you need antacids more than twice a week, if symptoms persist despite medication, or if you have trouble swallowing, food getting stuck, persistent nausea, unexplained weight loss, vomiting (especially with blood), or black stools. Chronic untreated reflux can damage the esophagus over time, leading to inflammation or a condition called Barrett’s esophagus, which carries a small but real cancer risk.

    One critical distinction: severe chest pain or pressure at night is not automatically heartburn. Heart attack symptoms — chest pressure, pain radiating to the arm, neck, or jaw, shortness of breath, cold sweats — can be mistaken for reflux, and vice versa. The Cleveland Clinic’s heartburn vs. heart attack guide walks through how to tell the difference. When in doubt at 3AM, err on the side of caution and get checked. It is always better to be embarrassed at the ER than wrong at home.

    Nighttime heartburn peaks around 3AM because you are flat, producing less saliva, and swallowing less — while a late dinner and evening alcohol are still sitting in your stomach. Prevent it by finishing dinner three hours before bed, elevating the head of your bed, and sleeping on your left side. Those three changes stop most 3AM attacks without any medication.

    Conclusion

    Heartburn at 3AM is not random and not something you have to accept as part of life. The causes are mechanical and fixable: eating too close to bedtime, reflux-trigger foods in the evening, lying flat, and sleeping on the wrong side. Start with the free fixes — earlier dinner, left-side sleeping, a raised bed head — and add an evening H2 blocker if you still get breakouts. Track what you ate on the nights it happens; the pattern usually reveals itself within a week or two. And if it keeps happening despite all of this, talk to your doctor, because persistent nighttime reflux is very treatable. For more practical health guides, browse our health section, learn about who writes our health coverage, or share your own nighttime remedies with us.

    Frequently Asked Questions

    Why does my heartburn always hit at 3AM specifically?

    It is a combination of timing and physiology. By 3AM, a late dinner is still partially digesting while you lie completely flat, saliva and swallowing are at their overnight lowest, and stomach acid production can peak during the night. That convergence is why the attacks cluster in the early-morning hours.

    How long before bed should I stop eating to prevent nighttime heartburn?

    Aim to finish your last meal at least three hours before lying down. If you sleep at 11PM, dinner should be done by 8PM. Large, fatty, or spicy meals may need even more lead time, and avoid evening snacking within that three-hour window.

    Does sleeping on my left side really help heartburn?

    Yes — the stomach sits mostly left of center, so left-side sleeping keeps the esophageal valve above the stomach’s acid pool. Right-side sleeping positions the valve below the acid line and tends to make reflux worse. It is a simple change worth testing for two weeks.

    Are antacids enough for nighttime heartburn, or do I need something stronger?

    Antacids neutralize acid on contact and work fast, but the relief lasts only an hour or two. For recurring nighttime attacks, an H2 blocker like famotidine taken before bed reduces acid production through the night. Frequent symptoms (more than twice a week) deserve a doctor visit to discuss daily treatment.

    How can I tell if 3AM chest burning is heartburn or something dangerous?

    Heartburn is typically a burning sensation rising from the stomach toward the throat, often with a sour taste. Heart attack signs include pressure or tightness in the chest, pain spreading to the arm, neck, or jaw, shortness of breath, and cold sweats. If you are unsure, treat it as an emergency and call 911.

    Can I just use extra pillows to raise my head?

    A stack of pillows bends your neck without meaningfully raising your stomach above your esophagus, and it can cause neck pain. A wedge pillow or bed risers that elevate the head of the whole bed by six to eight inches work much better because they raise your entire upper torso.

  • How Do I Know If I Need Stitches for a Kitchen Cut?

    How Do I Know If I Need Stitches for a Kitchen Cut?

    You are chopping vegetables, the knife slips, and now there is blood — a clean cut on your finger, bleeding steadily. Do you need stitches, or will a bandage do? This is one of the most common urgent-care questions, and getting it right matters: cuts that need stitches but do not get them heal with worse scarring, higher infection risk, and sometimes impaired function; cuts that do not need stitches but get them waste your evening and your copay. The decision comes down to observable features you can assess in your kitchen in two minutes. Here is exactly how to tell.

    The Stitches Checklist: Assess the Cut

    Run through these criteria — any “yes” leans toward professional closure. Depth: can you see yellowish fatty tissue, or deeper red muscle? If the cut gapes open revealing tissue layers below the skin, it needs stitches — surface-only cuts that stay closed on their own usually do not. Width: does the cut gape open more than about 1/4 inch, or do the edges not come together when you gently push them? Gapng wounds cannot heal cleanly without closure. Length: cuts longer than about 3/4 inch on the face, or longer than an inch elsewhere, generally benefit from stitches for cosmetic and functional healing. Location: cuts over joints (knuckles, knees) — where movement constantly reopens them; cuts on the face (cosmetic outcome matters enormously); cuts on the hands (function matters — tendons and nerves run shallow); and cuts through the lip border or eyebrow (alignment is cosmetically critical). Bleeding: steady bleeding that does not slow after 10-15 minutes of firm direct pressure suggests a deeper vessel involved. Contamination: dirty or ragged cuts (not your clean kitchen knife slice) need professional cleaning and evaluation regardless. Numbness or inability to move the finger normally after the cut — possible tendon or nerve involvement, needs urgent evaluation. Two or more “yes” answers, or any nerve/tendon sign, means go. The American Academy of Dermatology’s wound-care guidance covers closure decisions.

    The Golden Window: Timing Matters

    Stitches are most effective within 6-8 hours of the injury — this is the “golden window” when infection risk from closure is lowest and tissue is most cooperative. After 12-24 hours, most clinicians will not stitch a wound closed (the infection risk of sealing in bacteria outweighs the benefit), opting instead for delayed closure or healing by secondary intention with close monitoring. Facial cuts get slightly more leeway (up to 24 hours) because facial blood supply fights infection so effectively. The practical implication: do not “wait and see overnight” on a cut you suspect needs stitches — the decision expires. If it is evening and the cut looks stitch-worthy, go to urgent care now rather than sleeping on it. While waiting: apply firm direct pressure with a clean cloth, elevate the injured part above heart level, and do not keep peeking (like nosebleeds, clot disruption restarts bleeding). Once bleeding is controlled, cover loosely with a clean bandage for transport — do not apply creams, butter, or home remedies to a wound that may be stitched; clinicians need to see and clean it properly. Time your decision, not just your assessment.

    When a Bandage Is Enough: Home Wound Care Done Right

    Many kitchen cuts genuinely do not need stitches — clean, shallow, short cuts whose edges come together easily. Treat them properly and they heal beautifully. The protocol: stop the bleeding first (firm direct pressure, 10-15 minutes, elevation). Then clean: rinse under running water for several minutes — clean water irrigation is the single most effective infection prevention; mild soap around (not inside) the wound is fine. Skip the hydrogen peroxide and rubbing alcohol — they damage healing tissue and are outdated wound care. Apply a thin layer of petroleum jelly (not antibiotic ointment necessarily — plain petrolatum works as well for clean minor cuts and avoids allergy risk), then cover with an adhesive bandage or sterile gauze. Change the dressing daily or when wet/dirty. For small gaping cuts that just miss the stitches threshold, adhesive wound-closure strips (butterfly bandages) from the pharmacy bridge the gap effectively — clean, dry the skin, and apply across the cut to hold edges together. Watch for infection over the next week: increasing redness, warmth, swelling, red streaks, pus, fever, or worsening pain mean see a doctor promptly. Most minor kitchen cuts heal in 7-10 days with this care. More first-aid guidance in our health section.

    Special Situations: When the Rules Change

    Certain contexts override the standard checklist. Blood thinners (warfarin, apixaban, clopidogrel, even daily aspirin): bleeding lasts longer and the threshold for professional evaluation drops — call your doctor’s office or urgent care for guidance on any significant cut. Diabetes or immune suppression: infection risk is higher and healing slower — get borderline cuts evaluated rather than home-managing. Animal or human bites: always need professional evaluation — bite wounds carry specific infection risks (including rabies considerations for animal bites) and are generally not stitched closed immediately. Puncture wounds (nails, toothpicks): the small surface opening hides deep contamination — clean thoroughly, ensure tetanus vaccination is current, and watch closely for infection. Cuts from rusty or dirty objects: tetanus booster needed if it has been more than 5 years for a dirty wound (10 for clean). Finger cuts with nail involvement: the nail bed may need repair for proper regrowth. And any cut where you cannot fully clean out visible debris — get help rather than digging. When the situation has complicating factors, the ER or urgent care visit is cheap insurance against the complications that make simple cuts complicated.

    A kitchen cut likely needs stitches if it is deep enough to show fat or muscle, gapes wider than 1/4 inch, is long, crosses a joint or the face, will not stop bleeding after 15 minutes of pressure, or involves numbness or lost movement. Decide within the 6-8 hour golden window — do not wait overnight. Clean shallow cuts whose edges meet usually heal fine with proper bandaging at home.

    Conclusion

    The stitches decision is a two-minute assessment: depth, gaping, length, location, bleeding persistence, and nerve/tendon signs. When in doubt on a borderline cut, urgent care is the right call — a quick professional look beats days of wondering, and the golden window rewards promptness. For the clearly minor cuts, proper cleaning, petroleum jelly, and a fresh bandage heal as well as anything. Respect the knife, respect the clock, and keep the bandages stocked. If first-aid questions come up, reach out to us — and learn more about our practical health coverage. The Red Cross first aid app walks through wound assessment step by step.

    Frequently Asked Questions

    How long do I have to get stitches?

    The golden window is 6-8 hours for most wounds (up to 24 for facial cuts due to excellent blood supply). After 12-24 hours, clinicians usually will not close a wound primarily because of infection risk. Do not wait overnight on a cut you suspect needs stitches.

    Can I use butterfly bandages instead of stitches?

    For small, clean, shallow cuts that gape slightly — yes, adhesive closure strips work well. They cannot replace stitches for deep, wide, long, or high-tension wounds (joints, hands), or contaminated cuts. They are a bridge for borderline minor cuts, not a substitute for real closure.

    Should I put Neosporin on a cut?

    For clean minor cuts, plain petroleum jelly works as well as antibiotic ointment for healing, with less allergy risk. Antibiotic ointment has a modest edge for dirty wounds. The critical steps are cleaning and covering — the ointment choice is secondary.

    How do I know if a cut is infected?

    Watch for increasing redness, warmth, swelling, or pain after the first 48 hours (some initial redness is normal), red streaks spreading from the wound, pus or cloudy drainage, fever, or pain that worsens instead of improving. Any of these warrant prompt medical evaluation.

    Do I need a tetanus shot for a kitchen cut?

    If your tetanus vaccination is current (booster within 10 years for clean wounds, 5 for dirty wounds), no. If you are unsure of your status or it has been longer, get a booster — tetanus from kitchen cuts is rare but the consequence is severe and the shot is simple.

  • Why Does My Shoulder Hurt When I Sleep on My Side Every Night?

    Why Does My Shoulder Hurt When I Sleep on My Side Every Night?

    Every morning you wake up with a dull ache deep in your shoulder — the one you sleep on. It eases as the day goes on, but it is there again the next morning, night after night. Side-sleeping shoulder pain is one of the most common sleep complaints in adults over 35, and it has specific mechanical causes. The good news: it is usually a pressure and positioning problem, not a damaged joint, and it responds well to targeted changes. Here is why your shoulder hurts, how to fix your sleep setup, and when the pain signals something needing medical attention.

    Why Side Sleeping Hurts Shoulders

    The mechanics are straightforward compression. When you lie on your side, your entire upper-body weight — head, shoulder girdle, and part of your torso — presses down through the shoulder joint onto the mattress. The shoulder is the body’s most mobile and least stable joint: a shallow socket holding a large ball, dependent on muscles and tendons (especially the rotator cuff) for stability rather than bony structure. Prolonged compression through the night does three things: it compresses the rotator cuff tendons between the arm bone and the shoulder blade (subacromial compression — the same mechanism as impingement syndrome), it reduces blood flow to the already poorly vascularized tendon tissues, and it can compress the nerves and blood vessels passing through the shoulder region. A mattress that is too firm concentrates all this force on the small contact point of the shoulder; a pillow that is too low or too high misaligns the neck and cascades abnormal forces down into the shoulder. Over months and years, nightly compression can progress from morning soreness to chronic tendinopathy — the tendons thicken, weaken, and become painful with daytime use too. The AAOS shoulder resources describe this impingement mechanism in detail.

    Fix Your Sleep Setup Tonight

    Several changes, implementable tonight, directly address the compression. Pillow height is the first fix: your pillow must fill the gap between your ear and the mattress so your neck stays straight — too low and your head drops, dragging the shoulder into compression; too high and it jams upward. Side sleepers typically need a thicker, firmer pillow than back sleepers (4-6 inches, depending on shoulder width — broader shoulders need thicker pillows). Second, hug a body pillow or place a pillow in front of your chest and rest your top arm on it — this prevents the upper shoulder from rolling forward into internal rotation, the position that maximizes impingement compression. Third, the mattress question: if your shoulder cannot sink in at all, the joint takes the full load — a 2-inch soft topper on the shoulder zone (or a full medium-soft topper) lets the shoulder sink enough to distribute pressure. Fourth, try the “shoulder cutout” position: lie slightly forward of true side-lying (about 30 degrees toward stomach) with the bottom arm extended forward rather than trapped under you — this rolls the shoulder joint off direct compression. Fifth, alternate sides through the night if one shoulder is worse — even partial offloading helps. Test changes for a week each; morning pain is the scoreboard.

    Daytime Rehab: Strengthen What the Night Compresses

    Nightly compression is better tolerated by strong, mobile shoulders — daytime rehab builds that tolerance. The priority is the rotator cuff and scapular stabilizers: external rotations with a light resistance band (elbow tucked at your side, rotate forearm outward — 3×15 daily), scapular wall slides, band pull-aparts, and prone Y-T-W raises for the lower trapezius. These directly counter the impingement mechanics by improving the shoulder blade’s positioning and the cuff’s ability to center the joint. Add thoracic spine mobility — the hunched desk posture most people carry into bed rounds the shoulders forward, pre-loading the impingement before sleep even starts; doorway chest stretches and foam-roller thoracic extensions reverse this. Stretch the posterior capsule (the cross-body arm stretch) gently — tightness here pushes the ball of the joint upward into the impingement zone. Ten minutes daily, consistently, transforms most side-sleeping shoulder pain within 3-4 weeks — not by changing the sleep position but by making the shoulder resilient to it. Avoid the aggravators meanwhile: overhead pressing, heavy bench press, and sleeping with the arm overhead all compress the same structures. Our health section has more on joint-friendly strength routines.

    When Shoulder Pain Needs Medical Evaluation

    Positional pain that resolves with setup changes is mechanical; certain patterns need a doctor. Get evaluated if: the pain persists despite 3-4 weeks of proper sleep positioning and rehab exercises; pain is present during the day with normal activities (reaching overhead, lifting, dressing) — not just mornings; you have night pain that wakes you regardless of position (a red flag for more significant pathology); there is weakness — difficulty lifting the arm, dropping objects; the shoulder clicks, catches, or feels unstable; pain followed a specific injury or fall; or there is numbness/tingling down the arm (possible nerve involvement). The likely diagnoses in these cases: rotator cuff tendinopathy or partial tear, bursitis, labral tear, adhesive capsulitis (frozen shoulder — especially in the 40-60 age range, characterized by progressive stiffness), or acromioclavicular joint arthritis. Workup typically starts with physical exam maneuvers (often diagnostic) and may include ultrasound or MRI for persistent cases. Treatment ranges from physical therapy and corticosteroid injections to, for significant tears, arthroscopic repair — but the large majority of side-sleeping shoulder pain never reaches this stage when addressed early with positioning and strengthening.

    Side-sleeping shoulder pain is usually mechanical compression: body weight pressing the rotator cuff tendons through the night, worsened by wrong pillow height and too-firm mattresses. Fix it with proper pillow thickness, hugging a body pillow to prevent shoulder roll-forward, a softer sleep surface, and daily rotator cuff strengthening. Persistent daytime pain, weakness, night pain in all positions, or post-injury pain needs medical evaluation.

    Conclusion

    Your shoulder hurts because it spends eight hours nightly as a load-bearing joint it was never designed to be — but the fix is usually straightforward: pillow height that keeps the neck straight, arm positioning that avoids impingement, a surface that lets the shoulder sink, and daytime strengthening that builds tolerance. Implement the setup changes tonight and the exercises this week; most people see major improvement within a month. Reserve worry for the patterns that break the mechanical mold — daytime pain, weakness, injury, or pain that ignores position. Sleep should restore you, not injure you nightly. If shoulder issues persist, reach out — and learn more about our practical health coverage. The American Physical Therapy Association offers shoulder rehab exercise libraries.

    Frequently Asked Questions

    Should I stop sleeping on my side?

    Not necessarily — side sleeping is excellent for spinal alignment, snoring, and reflux. Fix the shoulder mechanics (pillow height, arm position, surface softness, strengthening) rather than abandoning the position. Only switch if pain persists despite proper setup.

    What pillow thickness is right for side sleepers?

    Generally 4-6 inches, enough to fill the ear-to-mattress gap and keep the neck straight — broader shoulders need thicker. Test it: have someone check your neck alignment from behind, or notice whether your neck feels bent up or down.

    Can side sleeping cause permanent shoulder damage?

    Chronic nightly compression can progress from soreness to tendinopathy over months/years if ignored — tendons thicken and weaken. But caught early, it is fully reversible with positioning and strengthening. The progression is slow and gives ample warning.

    Why does my shoulder hurt more some mornings than others?

    Usually reflects how long you spent on that side, mattress temperature (cold rooms stiffen tissues), previous day’s shoulder loading (workouts, overhead work), and pillow displacement during the night. Tracking the pattern reveals your specific triggers.

    When is shoulder pain a sign of a rotator cuff tear?

    Suspect tear with: weakness lifting the arm (especially overhead), pain after a specific injury or fall, night pain regardless of position, or a traumatic “pop” with immediate weakness. Degenerative partial tears can also develop gradually — persistent weakness despite rehab warrants imaging.